Australian Guidelines Every IMG Needs for the AMC MCQ
The Australian screening, immunisation, antibiotic, cardiovascular risk, alcohol, Medicare and mental health rules that decide AMC MCQ answers, with tables and worked questions.
Updated 20 October 202618 min readBy the AMC MCQs clinical team
Knowing the Australian guidelines for AMC MCQ questions is often what separates a pass from a near miss. The AMC CAT MCQ Examination expects you to manage patients the way a safe junior doctor would in Australia, and many questions have one best answer only because Australian guidance says so: which antibiotic is first-line, at what age a screening test starts, which vaccine is due, or how cardiovascular risk is calculated.
This guide covers the Australian frameworks the exam draws on most and where they differ from what many international medical graduates (IMGs) learned in India, Pakistan, the UK, the US and elsewhere. Every number comes from a current Australian primary source listed at the end; check them before you sit.
Key takeaways
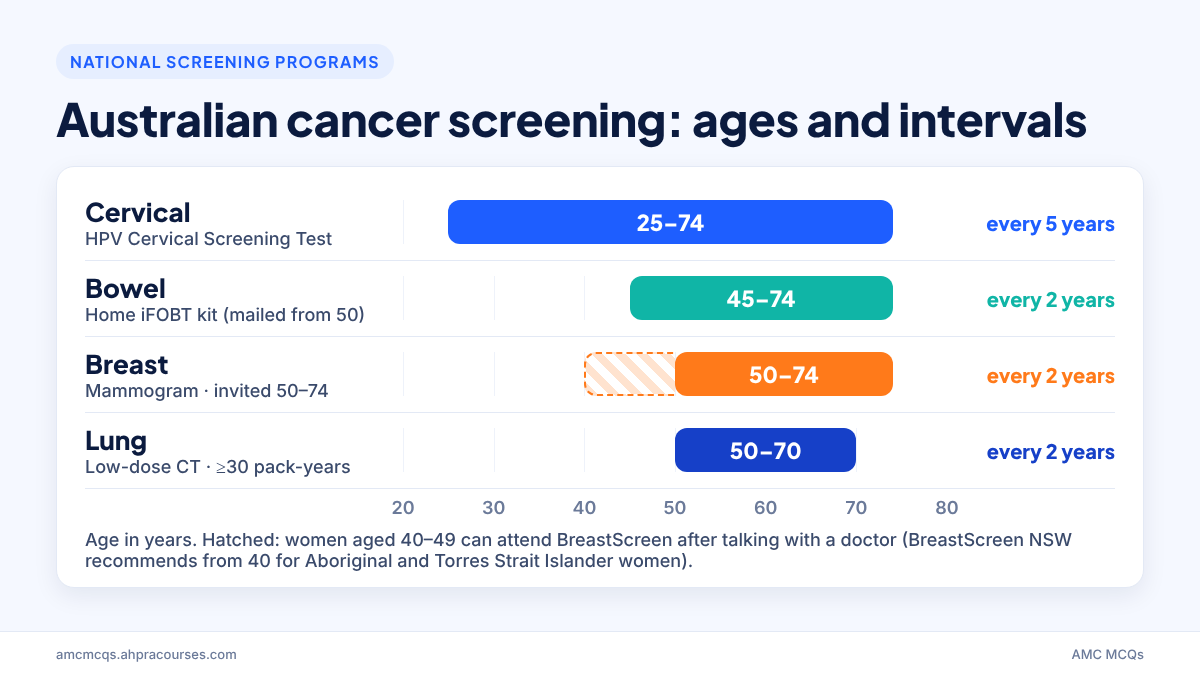
Screening: cervical HPV test every 5 years from 25 to 74; bowel iFOBT every 2 years from 45 to 74; mammogram every 2 years with invitations from 50 to 74; lung low-dose CT every 2 years for eligible people aged 50 to 70.
Antibiotics follow Therapeutic Guidelines: nitrofurantoin is first-line for acute cystitis, amoxicillin 1 g 8-hourly for low-severity pneumonia, and most sore throats, bronchitis and sinusitis need no antibiotic.
Cardiovascular risk is an absolute 5-year risk from the Aus CVD Risk calculator: high is 10% or more, intermediate 5% to under 10%, low under 5%.
Alcohol: no more than 10 standard drinks a week and no more than 4 on any day; a standard drink is 10 g of alcohol.
Aboriginal and Torres Strait Islander patients have earlier CVD assessment (from 30), extra vaccines, a 715 health assessment every 9 months and, where rheumatic fever risk is high, a lower threshold for treating sore throats and skin sores.
Why Australian guidelines decide AMC MCQ answers
Diagnosis is largely universal; investigation and management are not. When a stem asks for “the most appropriate next step”, the AMC is asking what is appropriate in Australia, with Australian drugs, programs, funding and law.
An answer that is standard practice in Lahore, Chennai, Lagos or London can be the distractor in an AMC question. You do not need to relearn medicine, just a defined set of Australian rules, practised until automatic.
The references that matter most are Therapeutic Guidelines (eTG), the Australian Immunisation Handbook and National Immunisation Program schedule, the RACGP Red Book, the national cancer screening programs, the 2023 Australian CVD risk guideline, the NHMRC alcohol guidelines, the MBS and PBS, and state public health and mental health law. Our AMC MCQ preparation resources guide explains how to use them alongside a question bank.
Australian cancer screening programs for the AMC MCQ
The national programs below apply to asymptomatic people at average risk. Anyone with symptoms needs diagnostic investigation, not a screening test, which is itself a common exam point.
Program
Who
Test
Interval
National Cervical Screening Program
Women and people with a cervix aged 25–74
Cervical Screening Test (HPV-based); self-collection is an option
Every 5 years
National Bowel Cancer Screening Program
People aged 45–74 (kits mailed at 50–74; people aged 45–49 can request one)
Immunochemical faecal occult blood test (iFOBT) at home
Every 2 years
BreastScreen Australia
Women aged 50–74 invited; women in their 40s and over 75 can attend after talking with a doctor
Screening mammogram
Every 2 years
National Lung Cancer Screening Program
Aged 50–70, no symptoms, at least 30 pack-years, and currently smoking or quit within the past 10 years
Low-dose CT (LDCT) of the chest
Every 2 years, depending on results
Australia’s four national cancer screening programs: ages, tests and intervals.
Cervical screening: HPV, not cytology
Australia replaced the Pap smear with the HPV-based Cervical Screening Test. Self-collection is available, which matters for under-screened women and patients who decline a speculum examination. Retrain your reflex: a 22-year-old asking for a “smear” is not yet eligible for routine screening, and a woman of 30 with a normal HPV result is not due again for 5 years.
Bowel screening: from 45, every two years
Kits are posted automatically from 50; people aged 45 to 49 can request one through the National Cancer Screening Register. A positive iFOBT needs referral for colonoscopy, not a repeat test.
Breast screening: invited from 50
Some programs, such as BreastScreen NSW, recommend that Aboriginal and Torres Strait Islander women start from 40. A woman with a breast lump, nipple discharge or skin change needs diagnostic assessment (triple assessment), not a screening mammogram.
Lung screening: the newest program
The National Lung Cancer Screening Program began in July 2025. A chest X-ray is not a screening test for lung cancer, and that is a likely distractor.
Exam tip: Calculate pack-years in the stem: packs per day multiplied by years smoked. Twenty cigarettes a day for 30 years is 30 pack-years; ten a day for 40 years is only 20 and does not meet the program criteria.
Immunisation schedule highlights
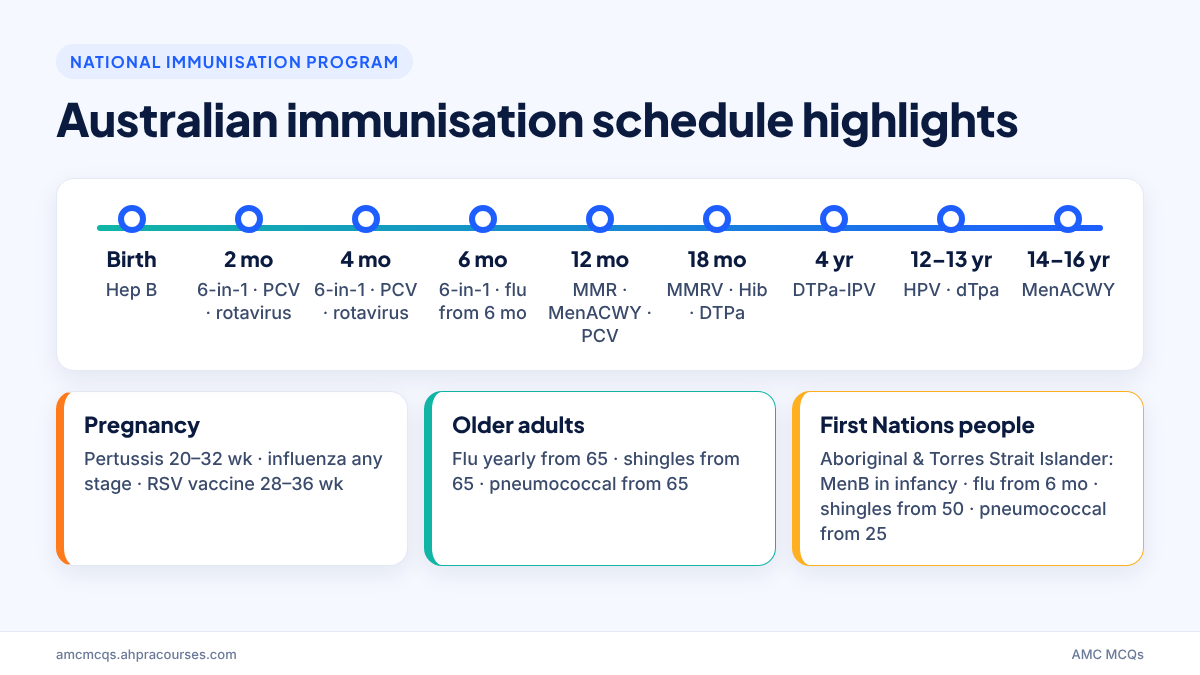
The National Immunisation Program (NIP) schedule is examined in child health, women’s health and population health. Learn the time points and the extras for pregnancy and for Aboriginal and Torres Strait Islander people.
Childhood and adolescent schedule
Age
Vaccines
Notes for the exam
Birth
Hepatitis B
Within 24 hours of birth (up to 7 days) if medically stable
Rotavirus dose 2 by 24 weeks 6 days; MenB for Aboriginal and Torres Strait Islander infants
6 months
DTPa-hepB-IPV-Hib
Extra pneumococcal dose for Aboriginal and Torres Strait Islander children and those with medical risk conditions; annual influenza from 6 months
12 months
MMR, meningococcal ACWY, pneumococcal conjugate
MenB for Aboriginal and Torres Strait Islander children
18 months
MMRV, Hib, DTPa
Hepatitis A for Aboriginal and Torres Strait Islander children in some states and territories
4 years
DTPa-IPV
Hepatitis A second dose where it applies
12–13 years (Year 7 at school)
HPV, dTpa
HPV is a single dose for most adolescents
14–16 years (Year 10 at school)
Meningococcal ACWY
Delivered through school programs; timing varies by state
Several states fund extra vaccines (Queensland, for example, funds meningococcal B more widely, and infant RSV protection with nirsevimab is delivered through state programs). Unless a stem says otherwise, answer from the national schedule.
Pregnancy
Pertussis (dTpa): one dose in every pregnancy, ideally between 20 and 32 weeks.
Influenza: recommended in every pregnancy, at any stage of gestation.
RSV: a single dose of the maternal RSV vaccine between 28 and 36 weeks, ideally at least 14 days before delivery, to protect the baby.
Live vaccines such as MMR and varicella are contraindicated in pregnancy; check rubella immunity before or after, not during.
Adults and older people
Influenza: annually from 65 years, and for all Aboriginal and Torres Strait Islander people from 6 months of age.
Pneumococcal: one dose of Capvaxive from 65 years, or from 25 years for Aboriginal and Torres Strait Islander adults.
Shingles (recombinant zoster vaccine, Shingrix): two doses 2 to 6 months apart from 65 years, or from 50 years for Aboriginal and Torres Strait Islander adults.
RSV (Arexvy): one dose from 75 years, or from 60 years for Aboriginal and Torres Strait Islander adults.
National Immunisation Program time points from birth to older age, with pregnancy and Aboriginal and Torres Strait Islander extras.
Practise Population Health & Ethics questionsExam-style single-best-answer questions with an explanation for every option. Start with the free sample.
Therapeutic Guidelines usually recommends a narrow-spectrum drug, a short course or no antibiotic at all. Broad-spectrum first choices such as amoxicillin-clavulanate, cephalosporins, macrolides or quinolones for routine infections are often the wrong AMC answer.
The table below follows the Therapeutic Guidelines summary table “Antibiotic prescribing in primary care” (2025). Doses are adult doses unless stated.
Condition
First-line in Australian guidelines
Key exam points
Acute cystitis, non-pregnant women
Nitrofurantoin 100 mg orally 6-hourly for 5 days
Many younger women improve without antibiotics; avoid ciprofloxacin and norfloxacin unless susceptibility testing rules out alternatives
Acute cystitis in pregnancy
Nitrofurantoin 100 mg orally 6-hourly for 5 days
Send urine culture before treatment and repeat 1–2 weeks after; avoid nitrofurantoin close to delivery
Low-severity community-acquired pneumonia
Amoxicillin 1 g orally 8-hourly, usually 5 days
Review on day 3; consider adding doxycycline if significant comorbidity and 48-hour follow-up is unlikely
Acute pharyngitis or tonsillitis
Symptomatic care for most (usually viral)
High risk of acute rheumatic fever: phenoxymethylpenicillin 500 mg 12-hourly for 10 days, or a single IM dose of benzathine benzylpenicillin 1.2 million units
Acute otitis media, children
Analgesia alone for most
Antibiotics if otorrhoea, under 6 months, under 2 years with bilateral infection, or systemically unwell: amoxicillin 15 mg/kg (max 500 mg) 8-hourly for 5 days
Acute bronchitis; acute rhinosinusitis
No antibiotic; symptomatic care
Antibiotics are rarely needed for rhinosinusitis
COPD exacerbation
Antibiotics only with more purulent sputum, increased volume and/or worse breathlessness
Amoxicillin 500 mg 8-hourly for 5 days, or doxycycline 100 mg daily for 5 days
Cellulitis without systemic features
Dicloxacillin or flucloxacillin 500 mg orally 6-hourly, usually 5 days
If streptococci suspected (nonpurulent or recurrent), phenoxymethylpenicillin 500 mg 6-hourly; cefalexin is often preferred in children
Impetigo
Limited (up to 2 sores): topical mupirocin for 5 days
Extensive, recurrent or bullous, or high rheumatic fever risk: oral di/flucloxacillin for 5 days
Human, cat or dog bites
Thorough wound cleaning; amoxicillin-clavulanate 875+125 mg 12-hourly for 5 days if indicated
Check tetanus status and consider rabies vaccination
Lactational mastitis
Non-antibiotic measures first
If no improvement after 24–48 hours: di/flucloxacillin 6-hourly
Exam tip: Trimethoprim does not appear as the first-line option for acute cystitis in the current Therapeutic Guidelines summary. If you learned “trimethoprim 300 mg for 3 days” from older resources, update it: the summary recommends nitrofurantoin 100 mg 6-hourly for 5 days.
Cardiovascular risk: think absolute, not single risk factors
Australia manages primary prevention of cardiovascular disease (CVD) by absolute 5-year risk, using the 2023 Australian guideline and the Aus CVD Risk calculator, rather than treating a cholesterol or blood pressure number in isolation.
Who to assess
People without known CVD aged 45 to 79.
People with diabetes from 35 to 79.
Aboriginal and Torres Strait Islander people from 30 to 79, with individual risk factors assessed from 18 to 29.
Do not use the calculator for people already known to be at high risk, such as moderate-to-severe chronic kidney disease or familial hypercholesterolaemia, or for people with established CVD.
Risk categories and management
5-year CVD risk
Category
Management
Reassess (if untreated)
10% or more
High
Prescribe blood pressure-lowering and lipid-modifying medicines unless contraindicated or inappropriate, plus lifestyle support
Formal reassessment not recommended
5% to under 10%
Intermediate
Consider blood pressure-lowering and lipid-modifying medicines after discussing benefits and harms
2 years
Under 5%
Low
Lifestyle; medicines not routinely recommended unless BP above 160/100 mmHg or total cholesterol above 7.5 mmol/L
5 years
Near a threshold, consider a higher category for First Nations people, people of Māori, Pacific Islander or South Asian background, and people with a family history of premature CVD or severe mental illness.
Alcohol guidelines and the standard drink
The NHMRC guidelines give three recommendations that you should be able to quote:
Healthy adults: no more than 10 standard drinks a week and no more than 4 standard drinks on any one day.
Children and young people under 18 should not drink alcohol.
People who are pregnant or planning a pregnancy should not drink alcohol; for breastfeeding, not drinking is safest.
An Australian standard drink contains 10 g of alcohol (a UK unit is 8 g). Standard drinks = litres × % alcohol by volume × 0.789, so a 750 mL bottle of 13% wine is about 7.7 standard drinks, and a bottle on three nights a week exceeds both limits.
Try 60 free AMC MCQ practice questionsTen from every domain, in tutor mode with full explanations. Create a free account in under a minute.
You do not need billing detail, but funding shapes “most appropriate” answers in population health questions.
Item
Current figure
Why it matters
PBS general patient co-payment
A$25.00 per script (from 1 January 2026)
Cost is a barrier to adherence for some patients
PBS concessional co-payment
A$7.70 per script
Applies to concession card holders
PBS Safety Net thresholds
A$1,748.20 general; A$277.20 concessional
After the threshold, scripts become cheaper or free for the rest of the year
MBS item 715
Aboriginal and Torres Strait Islander health assessment by a GP, claimable once every 9 months
The structured opportunity for screening, vaccination and risk assessment
PBS figures are current at the time of writing (October 2026) and are indexed; treat them as context, not facts to memorise.
Notifiable diseases and public health action
Each state and territory has its own notifiable disease list, and the Australian Government maintains the national list. Doctors must report suspected as well as confirmed cases to the state or territory health department, some by telephone.
Measles is the classic example. In Victoria it is an urgent notifiable condition that must be reported on suspicion by phone. Typical public health facts the exam can test:
Infectious from 24 hours before prodromal symptoms until 4 days after the rash appears.
Children with measles are excluded from school and children’s services until at least 4 days after rash onset.
Post-exposure prophylaxis: MMR vaccine within 72 hours of first exposure, or normal human immunoglobulin within 144 hours (6 days) for higher-risk contacts such as susceptible pregnant women, immunocompromised people and infants too young to be vaccinated.
After immunoglobulin, MMR or MMRV should not be given for at least 5 months.
For a suspected notifiable infection, “what else should you do?” is often answered by notifying the public health unit.
Aboriginal and Torres Strait Islander health
Do not assume a patient’s identity from appearance or name; ask, because it changes screening, vaccination and treatment thresholds:
CVD risk: assess from age 30 with the calculator (risk factors from 18), consider a higher category near a threshold, and reassess yearly or at least every 2 years.
Health assessment: the MBS 715 health assessment is available every 9 months and is the natural place for screening and vaccination.
Vaccines: MenB in infancy, an extra infant pneumococcal dose, hepatitis A in some jurisdictions, annual influenza from 6 months, pneumococcal vaccine from 25 and shingles vaccine from 50.
Breast screening: eligible from 40, and some programs (BreastScreen NSW, for example) recommend starting at 40.
Acute rheumatic fever risk: in high-risk settings, treat streptococcal sore throat with phenoxymethylpenicillin for 10 days or a single IM benzathine benzylpenicillin dose, and treat impetigo with an oral antibiotic rather than topical mupirocin alone.
Mental health law is set by each state and territory. In Victoria, for example, the Mental Health and Wellbeing Act 2022 commenced on 1 September 2023, replacing the Mental Health Act 2014. You need the shared principles, not section numbers:
Involuntary assessment or treatment requires a mental illness and, because of it, a need for treatment to prevent serious harm to the person or others.
There must be no less restrictive way of providing that treatment, so voluntary treatment is always considered first.
Involuntary orders are time-limited and reviewed by an independent body such as a Mental Health Tribunal.
People receiving compulsory treatment keep rights to information and to have their order reviewed.
A patient with acute psychosis who refuses admission and is at serious risk is a candidate for involuntary assessment; a distressed patient with capacity and no serious risk is not. Revise these scenarios in our mental health MCQ hub.
Where IMG habits differ from Australian answers
A common habit elsewhere
The Australian answer
Broad-spectrum antibiotics for sore throat, bronchitis or sinusitis
Symptomatic care for most; penicillin only for those at high risk of rheumatic fever
Trimethoprim or a quinolone for simple cystitis
Nitrofurantoin 100 mg 6-hourly for 5 days
Pap smear every three years from first sexual activity
HPV-based Cervical Screening Test every 5 years from 25 to 74
Chest X-ray to screen heavy smokers
Low-dose CT through the National Lung Cancer Screening Program for eligible people aged 50–70
Starting a statin because LDL cholesterol is “high”
Calculate absolute 5-year CVD risk first, unless the patient is already known to be high risk
Counting alcohol in UK units of 8 g
Australian standard drinks of 10 g; limits of 10 a week and 4 a day
Treating a suspected measles case without telling anyone
Notify the public health unit on suspicion, by phone
Add any of these that match your reflexes to your error log; our guide to how to pass the AMC MCQ first attempt shows how to build one.
Worked questions on Australian guidelines
Try each original question before opening the explanation.
A 26-year-old woman presents to a general practice with 2 days of dysuria and urinary frequency. She has no fever, loin pain or vaginal discharge, is not pregnant and has normal kidney function. A urine dipstick is positive for leucocytes and nitrites. According to current Australian guidelines, which is the most appropriate antibiotic if treatment is chosen?
Trimethoprim 300 mg orally once daily for 3 days
Ciprofloxacin 500 mg orally 12-hourly for 3 days
Amoxicillin-clavulanate 875+125 mg 12-hourly for 5 days
Nitrofurantoin 100 mg orally 6-hourly for 5 days
Cefalexin 500 mg orally 12-hourly for 7 days
Show answer and explanation
Answer: D. The Therapeutic Guidelines primary care summary lists nitrofurantoin 100 mg 6-hourly for 5 days as first-line for acute cystitis in non-pregnant adult women, and notes that many younger women improve without antibiotics. A reflects older practice and is no longer the listed first-line choice. B is wrong because quinolones are reserved for when susceptibility testing rules out alternatives. C is an unnecessarily broad-spectrum choice for uncomplicated cystitis and is not the listed first-line drug. E is not the first-line recommendation for this patient and the duration is longer than needed.
A 62-year-old man attends for a check-up. He smoked 20 cigarettes a day for 35 years and stopped 6 years ago. He has no cough, haemoptysis, weight loss or other symptoms, and examination is normal. He asks about lung cancer screening. What is the most appropriate advice?
Refer for a low-dose chest CT under the national program
Arrange a plain chest X-ray now and repeat it every year
Explain that he is ineligible because he no longer smokes
Arrange sputum cytology on three morning samples now
Arrange a contrast CT of the chest and upper abdomen now
Show answer and explanation
Answer: A. He is 50 to 70, asymptomatic, has 35 pack-years (more than 30) and quit within the past 10 years, so he meets the National Lung Cancer Screening Program criteria for low-dose CT, usually repeated every 2 years depending on the result. B and D are not effective screening tests. C is wrong because people who quit within the past 10 years remain eligible. E uses a higher radiation dose and is a diagnostic test, not screening.
A 38-year-old Aboriginal man sees his GP for a 715 health assessment. He smokes, has no known cardiovascular disease or diabetes, and his blood pressure is 138/86 mmHg. His kidney function and urine albumin-to-creatinine ratio are normal. What is the most appropriate approach to his cardiovascular risk?
Defer formal risk calculation until he reaches 45 years
Calculate risk only if he later develops type 2 diabetes
Arrange a coronary artery calcium score as the first test
Start a statin now because of his Aboriginal background
Calculate 5-year risk now using the Aus CVD Risk tool
Show answer and explanation
Answer: E. The 2023 Australian guideline recommends using the Aus CVD Risk calculator for Aboriginal and Torres Strait Islander people from age 30, and considering a higher category if his result is near a threshold. A applies the general population starting age of 45. B is wrong because diabetes lowers the starting age to 35 but is not required. C is not recommended for population screening and is only considered when treatment decisions are uncertain. D skips the risk assessment; treatment decisions follow absolute risk.
A 30-year-old woman who is 16 weeks pregnant was in a waiting room with a child later confirmed to have measles 4 days ago. She has no documented MMR doses and her measles serology is negative. She is well. What is the most appropriate management?
Give a dose of MMR vaccine today and repeat it in 4 weeks
Reassure her and advise MMR vaccination after she gives birth
Give normal human immunoglobulin and notify public health
Start oral aciclovir for 7 days and review her in one week
Arrange admission for isolation until 21 days after exposure
Show answer and explanation
Answer: C. She is a susceptible pregnant contact within 144 hours (6 days) of exposure, so normal human immunoglobulin is recommended, and measles is an urgent notifiable condition. MMR should then be given after delivery. A is wrong because MMR is a live vaccine and is contraindicated in pregnancy (and she is also past the 72-hour window). B ignores effective post-exposure prophylaxis that is still available. D is wrong because aciclovir has no role against measles. E is unnecessary for a well contact; public health will advise on exclusion and monitoring.
How to study Australian guidelines for AMC MCQ preparation
Keep one “Australian differences” page and add every rule that differs from your training. Learn numbers in clusters (screening, immunisation, eTG, CVD, alcohol), read the eTG primary care summary and the NIP schedule once in full, and mix population health questions into every timed block. Programs change, so always use current sources rather than old notes.
The AMC expects current Australian practice: Therapeutic Guidelines (eTG) for prescribing, the Immunisation Handbook and NIP schedule, the RACGP Red Book, the national screening programs, the 2023 CVD risk guideline and the NHMRC alcohol guidelines.
What are the cancer screening ages in Australia?
Cervical screening with an HPV-based test every 5 years from 25 to 74; bowel screening with a home iFOBT every 2 years from 45 to 74; screening mammograms every 2 years with invitations from 50 to 74; and low-dose CT lung screening every 2 years for eligible people aged 50 to 70 with a significant smoking history.
What is the first-line antibiotic for a simple UTI in Australia?
For acute cystitis in non-pregnant adult women, the Therapeutic Guidelines primary care summary recommends nitrofurantoin 100 mg orally 6-hourly for 5 days. The same regimen is listed in pregnancy, with urine culture before and after.
How is cardiovascular risk assessed in Australia?
With the Aus CVD Risk calculator, which estimates absolute 5-year risk. It is used from 45 to 79 in the general population, from 35 in people with diabetes and from 30 in Aboriginal and Torres Strait Islander people. High risk is 10% or more, intermediate 5% to under 10%, and low under 5%.
What are the Australian alcohol guidelines?
Healthy adults should drink no more than 10 standard drinks a week and no more than 4 on any one day. People under 18 and those who are pregnant or planning pregnancy should not drink, and not drinking is safest when breastfeeding. A standard drink contains 10 g of alcohol.
Do I need to know state Mental Health Acts for the AMC MCQ?
You need the shared principles rather than section numbers: involuntary treatment needs a mental illness, a risk of serious harm, a need for treatment and no less restrictive option, and orders are time-limited and reviewed by a tribunal.
Are Aboriginal and Torres Strait Islander health guidelines tested?
Yes. Expect questions on CVD risk assessment from 30, the 715 health assessment every 9 months, extra vaccines, breast screening from age 40, and treating sore throats and skin sores where rheumatic fever risk is high.
Turn this guide into marks
Answer exam-style AMC MCQs on this topic with an explanation for every option. 60 questions are free.
The Australian consent, confidentiality and mandatory reporting rules behind AMC ethics questions, plus biostatistics and screening worked step by step with four original practice…
Every AMC MCQ cost in one place, from the A$642 portfolio and A$2,920 authorisation to ECFMG verification, plus step-by-step Pearson VUE booking, change and…