
How to Build an AMC MCQ Study Plan Around a Full-Time Roster
Three complete AMC MCQ study plans (6 months, 3 months and 6 weeks) with weekly hours for working doctors, blueprint-weighted domain time, question targets…
Read the guideSeventeen practical tactics to pass the AMC CAT MCQ first time, from 84-second pacing and forward-only answering to error logs, mock analysis and a final 14-day plan.

If you want to pass the AMC MCQ first attempt, knowledge alone is not enough. The AMC Computer Adaptive Test (CAT) MCQ Examination gives you 150 single-best-answer questions in one 3.5-hour session, delivers them one at a time, and never lets you go back. That format punishes slow reading, second-guessing and gaps in Australian practice far more than it punishes a missing fact.
This guide gives you 17 specific tactics that working international medical graduates (IMGs) can apply from today: pacing at 84 seconds per question, a forward-only answering routine, how to guess well, an error log that actually changes your score, how to read your mocks, a day-by-day plan for the final two weeks, and an exam-day routine. It finishes with the most common reasons capable doctors fail, so you can avoid them.
A first-attempt pass is worth planning for because every attempt costs time and money. At the time of writing (October 2026) the CAT MCQ authorisation fee is A$2,920, on top of the A$642 portfolio establishment fee you paid at the start. Confirm current fees on the AMC website before you budget.
Time matters too. Results are released at 4.00pm (AEST/AEDT) on the Friday three weeks after your exam, and you cannot apply for another exam until your scheduled result arrives. A fail costs a new fee, a new authorisation and usually months. Our AMC MCQ fees, booking and dates guide explains the authorisation and rescheduling rules in full.
The AMC reports your result on a scale of 0 to 500, and the pass mark is 250. That is a single pass point for every candidate, regardless of cohort or which questions you received. A score of 250 is not the same as answering 50% correctly, because the adaptive test weights your responses by the difficulty of the calibrated questions you answered. The AMC has advised candidates of an update to the pass standard for 2026 sittings; the reported pass mark is still 250, so check the current specifications. Our AMC MCQ pass mark and scoring explainer walks through how the scale works.
You do not need perfection. You need consistent, safe, Australian-standard decisions across all six domains at a steady pace.
The first six tactics are about the test itself; they protect marks you have already earned.
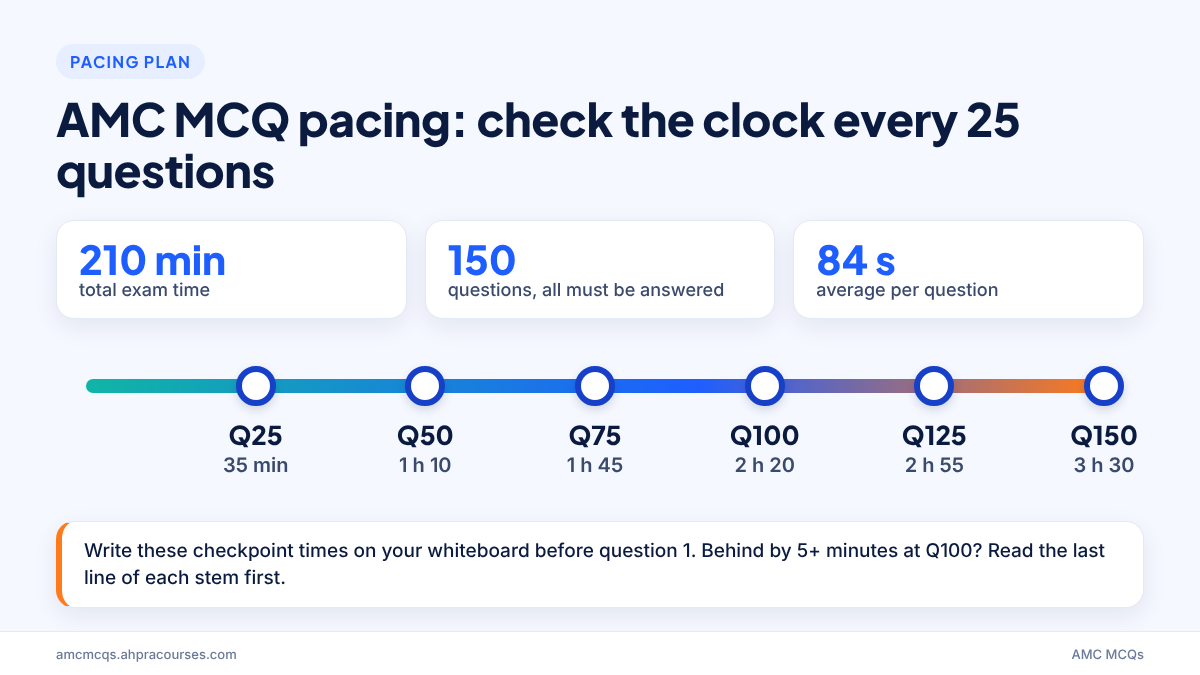
3.5 hours is 210 minutes. Divided by 150 questions, that gives you 84 seconds each. Some questions (a straightforward vaccine schedule item) take 40 seconds; others (a long stem with a table of results) take two minutes. The average is what matters.
The exam platform shows a timer clock. Instead of checking it after every question, which wastes attention, use fixed checkpoints every 25 questions.
| After question | Time used (84 s pace) | Time remaining | If you are behind |
|---|---|---|---|
| 25 | 35 min | 2 h 55 min | Normal to be 2–3 minutes slow while settling in |
| 50 | 1 h 10 min | 2 h 20 min | Cap any question at 2 minutes from here |
| 75 | 1 h 45 min | 1 h 45 min | Halfway: time and questions should match |
| 100 | 2 h 20 min | 1 h 10 min | More than 5 minutes behind: read the last line first on every stem |
| 125 | 2 h 55 min | 35 min | Under 30 minutes left: about 70 seconds per question |
| 150 | 3 h 30 min | 0 | Every question answered |
Write the checkpoint times on the whiteboard provided before you start question 1, so you compare two numbers instead of doing arithmetic under pressure.
The AMC specifications state that each question must be answered before the next is delivered, and that once a question has been answered you cannot go back and change your response. There is no flag-and-review button. Many IMGs have spent years in paper exams where returning to doubtful questions was a core strategy; that habit has to go.
Use the same four-step routine on every item:
You must complete all 150 items. The specifications warn that failing to do so may leave too little information for a reliable score, and the result may be recorded as “Fail – insufficient data to obtain result”. Running out of time is one of the few ways to fail an exam you were on track to pass.
If you reach 15 minutes remaining with more than 12 questions left, switch to rapid mode: last line, key finding, best option, next. A quick educated answer is far better than an unseen question.
Marks are not deducted for incorrect answers, and the platform will not let you skip, so on every hard question you will make a choice anyway. Make it an informed one:
In the CAT, the first question is chosen at random; a correct answer leads to a harder question and an incorrect answer to an easier one, and your ability estimate is recalculated after each response. That means a strong candidate will feel the exam getting harder. Feeling stretched is often a sign you are doing well, not badly.
There is a second reason to ignore difficulty. At least half of the questions come from a pool of previously calibrated items, and the rest are new questions being calibrated before they are used for scoring. Some items do not count, and you cannot tell which. The bizarre question that throws you may be one of them. Give it your best 84 seconds and leave it behind.
Because you cannot return, a question you know you got wrong can follow you for the next five. Practise a reset ritual in every timed block: one slow breath out, shoulders down, eyes on the next stem’s last line.
Exam tip: Practise under the real rules from the start of your preparation, not just in the final month. Our timed blocks run at 84 seconds per question, and the full 150-question mock uses a 3.5-hour countdown with forward-only navigation, so the exam format feels routine by the time you sit it.
The AMC tests the disease process, clinical examination and diagnosis, investigation, and therapy and management. Questions are also built around three clinician tasks: data gathering, data interpretation and synthesis, and management. Recognising which task a stem is testing narrows your options quickly.
| Clinician task | Typical last line | What the best answer usually looks like |
|---|---|---|
| Data gathering | “What is the most important question to ask?” / “Which examination finding would be most helpful?” | The item that separates the two most likely diagnoses or reveals a red flag |
| Data interpretation and synthesis | “What is the most likely diagnosis?” / “What does this result indicate?” | The diagnosis that explains every finding, including the odd one |
| Management | “What is the most appropriate next step?” / “What is the most appropriate initial treatment?” | The safest correct action at this moment, in this setting, under Australian guidance |
“Next step” depends on where the patient is. The same chest pain is managed differently in a metropolitan emergency department, a remote clinic and a GP surgery. Read for clues such as “rural hospital”, “general practice”, “nursing home” or “telehealth”, and choose the action that is realistic there.
Setting also means country. The AMC expects Australian practice: Therapeutic Guidelines (eTG) antibiotic choices, the National Immunisation Program schedule, national screening programs and Australian law on consent and confidentiality. Our guide to Australian guidelines for the AMC MCQ sets out where these differ from what many IMGs learned at home.
Several options in an AMC question are often defensible. The best answer is the one that is correct for this patient now, not the eventual definitive treatment. A stable patient with suspected ectopic pregnancy needs confirmation before surgery; an unstable one needs resuscitation and theatre. Ask yourself, “What would a safe intern-level doctor in Australia do first?”
A 31-year-old woman presents to a general practice with 10 minutes of generalised urticaria, lip swelling, wheeze and light-headedness after a bee sting in her garden. Her blood pressure is 84/50 mmHg and pulse 124/min. What is the most appropriate immediate management?
Answer: B. This is anaphylaxis with hypotension and bronchospasm. Intramuscular adrenaline (0.01 mg/kg, maximum 0.5 mg in adults, using 1 mg/mL adrenaline) into the anterolateral thigh is the first and most important treatment, followed by lying her flat, calling for help and giving oxygen and fluids. A is wrong because corticosteroids act too slowly and do not treat the acute reaction. C treats wheeze only and delays adrenaline. D is unsafe because antihistamines do not reverse airway oedema or shock. E is wrong because a 1 mg intravenous bolus is a cardiac arrest dose and risks arrhythmia in a patient with a pulse. The tactic: when the stem signals an immediate threat, the answer is the action that removes it.
These tactics turn study hours into marks.
The AMC blueprint allocates questions by patient group. In a 150-question exam the approximate numbers are:
| Domain | Weight | About how many questions |
|---|---|---|
| Adult health – Medicine | 30% | about 45 |
| Adult health – Surgery | 20% | about 30 |
| Women’s health (obstetrics and gynaecology) | 12.5% | about 19 |
| Child health | 12.5% | about 19 |
| Mental health | 12.5% | about 19 |
| Population health and ethics | 12.5% | about 19 |
The four smaller domains together make up half the exam. An internal medicine specialist who neglects obstetrics, paediatrics, psychiatry and ethics is putting about 75 questions at risk. Allocate study time roughly in proportion to these weights, then add extra time to whichever domain your analytics show is weakest. Our AMC MCQ study plan converts these weights into weekly hours for working doctors.
Doing thousands of questions without reviewing them properly is the most common wasted effort in AMC preparation. For every question you get wrong, or get right by guessing, record one line:
| Error type | What it looks like | The fix |
|---|---|---|
| Knowledge gap | You had never learned the fact or threshold | Learn it from an Australian source; make one flashcard |
| Non-Australian answer | Right at home, wrong here (drug, schedule, screening age) | Add to a dedicated “Australian differences” page and re-read weekly |
| Misread stem | Missed “pregnant”, “child”, “next step”, “most likely” | Re-run the four-step routine; underline the last line on the whiteboard |
| Sequencing error | Chose the definitive step instead of the next step | Ask “safest correct now?” before every management answer |
| Changed from correct | Your first choice was right, then you switched | Only change a prediction when you find a specific fact in the stem |
| Time pressure | Rushed because you were behind | Practise checkpoints in every timed block |
After 300 to 500 questions, count the categories. If a third of your errors are “non-Australian answer”, targeted Australian revision will help more than textbooks.
A correct answer reached for the wrong reason is a future wrong answer. Read why each distractor is wrong; one well-explained question can teach you five facts.
A sensible progression: untimed tutor mode by domain in the first third of your preparation, 25 to 50-question timed mixed blocks in the middle third, and full 150-question mocks in the final third.
A mock exam is a diagnostic test, not a ritual. Sit at least two full 150-question mocks under real conditions: the same time of day as your booking, 3.5 hours, no phone, forward-only navigation. Then spend at least as long reviewing it as you spent sitting it.
Judge readiness from a trend across mocks and timed blocks and stable performance in all six domains, not from one score.
Facts learned in month one fade by month four unless revisited. Redo incorrect questions after one week and again after a month, re-read your “Australian differences” page weekly, and bookmark questions with numbers you keep forgetting.
The final fortnight is for consolidation, not new textbooks.
| Days before exam | Focus | Daily target |
|---|---|---|
| 14–12 | Full mock 1 under real conditions, then a complete review | Mock day, then 2 review days |
| 11–9 | Weakest two domains from the mock | 60–80 timed questions plus error-log review |
| 8–7 | Australian differences: screening, immunisation, eTG, law and ethics | 40 timed questions plus your differences page |
| 6 | Full mock 2 (or a second set of 150 mixed questions) | Mock and timing review |
| 5–3 | Redo incorrect questions; high-yield numbers; light mixed blocks | 50 questions, focus on accuracy |
| 2 | Light review only; confirm venue, travel and ID | 20–30 questions maximum |
| 1 | Rest; no new content; early night | None |
If you work night shifts, try to swap your final week to days. You want your body clock to be alert at the time of your booking, not at 3am.

Prioritise your error log (“non-Australian answer” entries first), screening ages, the immunisation schedule, eTG first-line antibiotics, emergency algorithms (anaphylaxis, sepsis, acute asthma, diabetic ketoacidosis, postpartum haemorrhage), consent and confidentiality rules, and biostatistics formulas.
A calm exam morning is built the week before: check your Pearson VUE confirmation, the venue and the real journey time.
Exam tip: Read the latest AMC CAT MCQ Examination Specifications and the exam events page in the week of your exam. Rules on identification and conduct are set by the AMC and Pearson VUE, and the current documents always override any guide, including this one.
Expect to feel uncertain often; an adaptive test keeps searching for the edge of your ability. You can get many questions wrong and still pass, but you cannot let one bad question wreck the next ten.
A 29-year-old woman presents to an emergency department with 7 weeks of amenorrhoea and mild left iliac fossa pain. She has had light vaginal spotting since yesterday. Her pulse is 82/min, blood pressure 118/76 mmHg, and her abdomen is soft with mild left-sided tenderness. A urine pregnancy test is positive. What is the most appropriate next step?
Answer: C. She is haemodynamically stable with a possible ectopic pregnancy, so the next step is to locate the pregnancy: transvaginal ultrasound together with a quantitative serum hCG (and blood group, so anti-D can be considered if she is RhD negative). A would be right only if she were unstable or had signs of significant intraperitoneal bleeding. B delays diagnosis in a potentially life-threatening condition and a qualitative urine test adds nothing. D is premature because methotrexate is given only once an ectopic pregnancy is diagnosed and criteria are met. E exposes a possible pregnancy to radiation and is not the right test. The tactic: for a stable patient, “next step” is usually the investigation that confirms the diagnosis, not the definitive treatment.
Most doctors who fail the AMC MCQ are competent clinicians. They usually fail for predictable, fixable reasons:
A question bank is the closest thing to the real exam you can practise daily. Used well, it shows what you do not know, trains your pace and builds Australian reflexes.
If you are still choosing materials, our AMC MCQ preparation resources guide compares official AMC resources, Australian guidelines and question banks for different budgets. For the conditions most worth mastering in each domain, see our AMC MCQ high-yield topics. You can compare the one-time question packs on our pricing page.
Our questions are original and written to the AMC blueprint; they are not recalls, and this site is not affiliated with the AMC.
Yes. Many IMGs pass first time, including doctors studying while working full time. The candidates who do usually study to the AMC blueprint, practise under timed, forward-only conditions, learn Australian guidelines rather than home-country practice, and review every mistake with an error log.
On average 84 seconds: the exam gives 3.5 hours (210 minutes) for 150 questions. Use checkpoints every 25 questions, aiming to finish question 50 by 70 minutes and question 100 by 140 minutes, rather than checking the clock after every item.
No. You must answer each question before the next is delivered, and once you answer you cannot go back to change it. That is why a forward-only routine of reading the last line first, predicting, eliminating and committing is essential.
Yes. The AMC states that marks are not deducted for incorrect answers, and you cannot move on without answering. Eliminate unsafe or non-Australian options first and choose the safest correct action for the setting in the stem.
The AMC expects candidates to complete all 150 items. If you do not, there may not be enough information to produce a reliable score, and the result may be recorded as “Fail – insufficient data to obtain result”. Keep to your pace so this never happens.
There is no official number. Quality of review matters more than volume, but most well-prepared candidates complete a few thousand exam-style questions across all six domains, plus at least two full 150-question timed mocks, and review every incorrect answer.
Usually the opposite. The test is adaptive: a correct answer leads to a harder question and an incorrect one to an easier question. Some items are also new and unscored. Do not try to judge your performance from difficulty during the exam.
Answer exam-style AMC MCQs on this topic with an explanation for every option. 60 questions are free.
Three complete AMC MCQ study plans (6 months, 3 months and 6 weeks) with weekly hours for working doctors, blueprint-weighted domain time, question targets…
Read the guideThe Australian screening, immunisation, antibiotic, cardiovascular risk, alcohol, Medicare and mental health rules that decide AMC MCQ answers, with tables and worked questions.
Read the guideWhich AMC MCQ preparation resources are worth your time: the official AMC specifications and app, the Australian guidelines that decide the best answer, how…
Read the guide
